

What’s broke and why it keeps happenin’
Too many dentures wobble or rub because the jaw relation wasn’t caught right to begin with. Folks hand over impressions or guess at vertical dimension and that’s where trouble starts. If you want tighter fits and less back-and-forth, start by fixin’ the source — the jaw relation record — and don’t try to paper over it with adjustments later: jaw relation record.

How I know this and why you can trust it
I’ve been in small clinics and labs, tappin’ on frames and sittin’ in on fittings long enough to see the same mistakes repeat. That practical time behind the bench taught me what measurements matter and what folks often skip. When practitioners bring objective motion data into planning, the results stop feelin’ like guesswork.
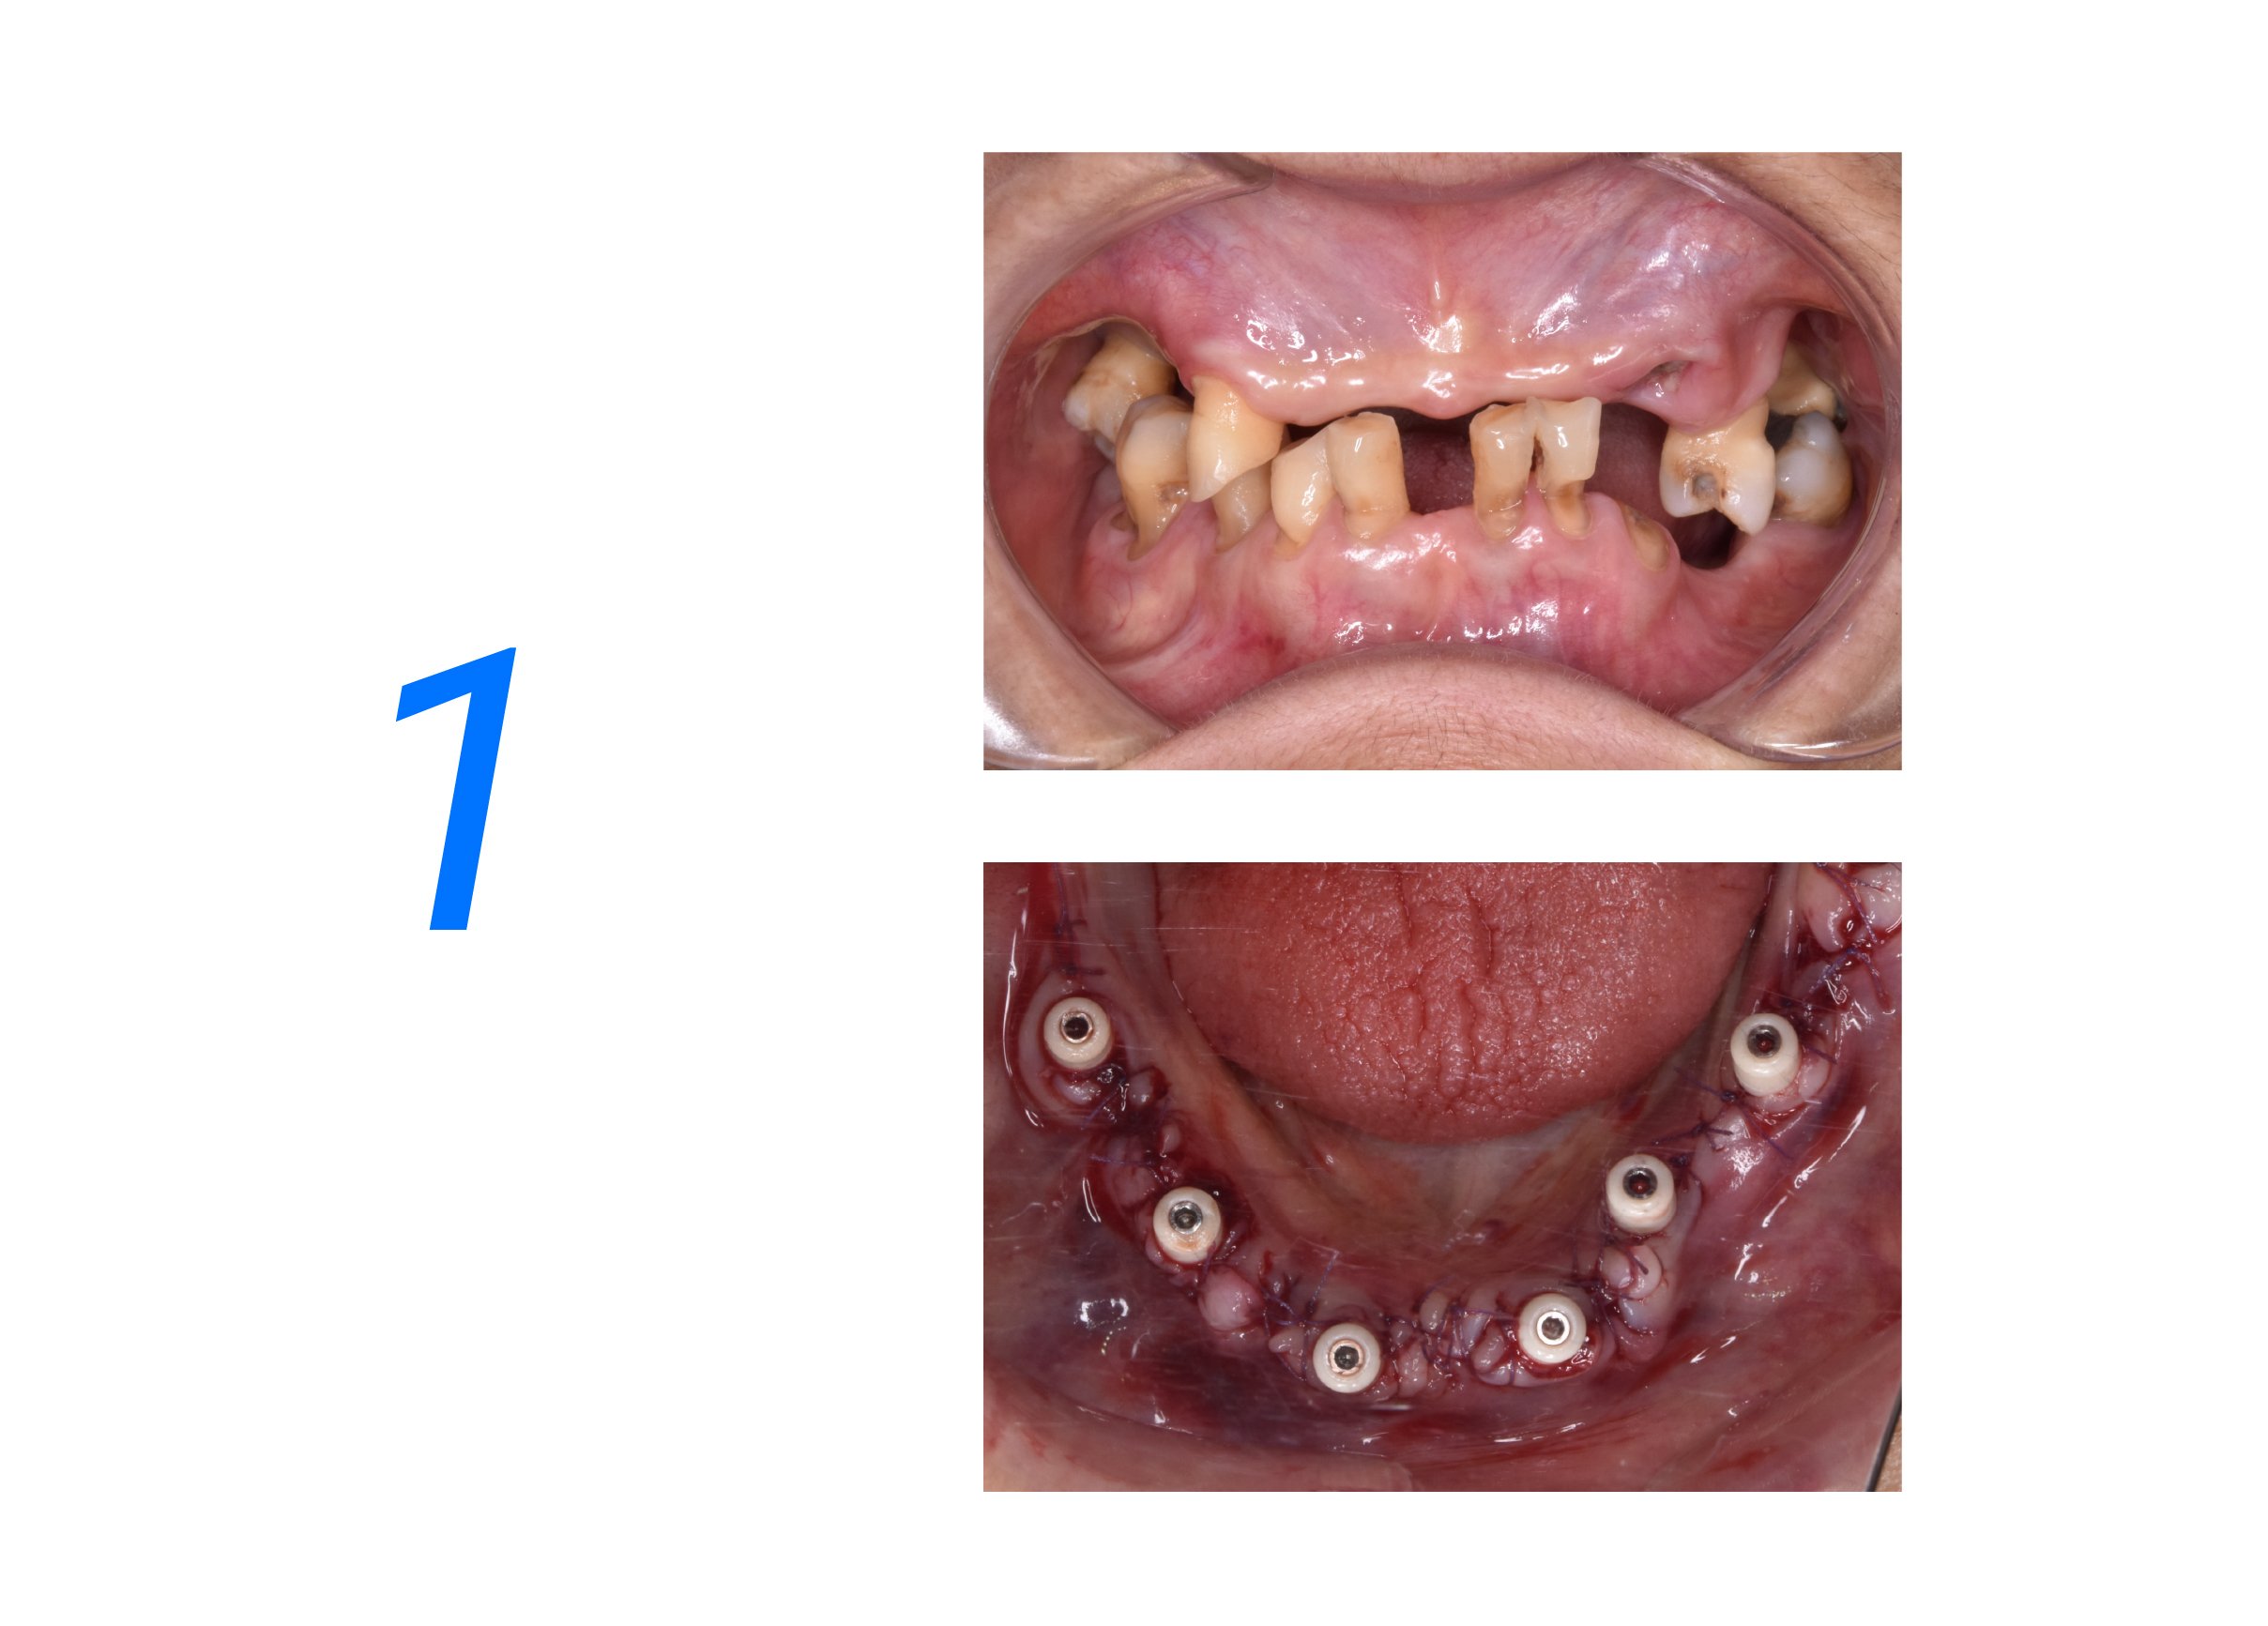
Where digital photogrammetry steps in
Digital photogrammetry maps the jaw’s positions without bulky plates. It lets you document centric relation, vertical height, and functional ranges while the patient actually moves. That means the cast you make, the setup you check, and the finished prosthesis all line up with how the jaw behaves, not how someone thought it behaved.
Real-world anchor and a simple demonstration
At the American Dental Association annual meeting in Chicago I watched live demos of jaw motion capture, and the result was clear: when motion data’s paired with photos and models, fit errors drop. That one show made the advantages plain to a bunch of clinicians who’d been muddlin’ along the old way.
Step-by-step, problem-driven workflow
Pick the problem you see: unstable lower denture, premature posterior contact, or collapsed vertical. Capture a baseline photo set of the arches, record functional movements, and tie those photos to the scanned models. Use the motion-and-photo set to set occlusal planes and vertical dimension, then verify with a trial flange. If the trial glides right through excursions, you got a winner. If not, pinpoint whether it’s a recording error, soft-tissue interference, or a lab transfer mistake.
Common potholes to dodge
Don’t skip calibration before capture. Don’t let soft-tissue rest mask functional relations. Don’t assume a single static bite fixes dynamic issues. And don’t hand off ambiguous files to the lab — annotate positions and movements plainly so the technician knows which frame represents centric, which shows protrusion, and which is maximal opening.
Alternatives and when to pick ’em
Traditional interocclusal records still work for some simple cases. Intraoral scanners give detailed surfaces but can miss dynamic relation unless you add motion capture. For complex neuromuscular patterns, combine surface scans with photogrammetry and motion data. Use the simpler route when the patient’s anatomy is straightforward and the functional envelope is small; choose the combined digital route when movement matters.
How this changes what you deliver
When you plan from documented motion and photos, adjustments go down and patient comfort goes up. You stop chasin’ occlusion and start matchin’ behavior. That’s practical; patients feel it right away and labs waste less material on remakes.
Wrap-up that ties it all together
Fix the measurement mistakes first, use photos and motion to lock in relations, and keep checks simple and direct. That approach cuts repeat visits and gives folks dentures that behave like natural teeth. For teams deployin’ dependable capture and clear file transfer, SHINING 3D DENTAL offers systems that fit into that workflow without fuss, so clinics and labs can focus on what matters — the patient’s fit and function.